Your baby has arrived weeks too early. They’re so tiny you’re afraid to touch them. What happens next?
For many parents, the joy of childbirth is suddenly overshadowed by fear when their baby arrives prematurely.
Will the baby breathe properly? Will they be able to feed? Will they survive?
A baby born before 37 completed weeks of pregnancy is considered premature. The earlier the birth, the greater the risk of complications, although the baby’s condition and the care available also matter.
But, a premature baby doesn’t always need an incubator to stay warm. Sometimes, a parent’s chest can provide that lifesaving warmth.
It’s called ‘kangaroo mother care’, and it is one of the most important ways for improving survival among premature and low-birth-weight babies.
Holding a baby skin-to-skin, with appropriate clinical supervision, helps maintain body temperature and supports breastfeeding. For eligible babies, it can begin soon after birth, even while other medical care continues.
Some premature babies also need help breathing. Others cannot yet coordinate sucking and swallowing and may need expressed breast milk through a feeding tube. Preventing infections and recognising complications early are equally important.
And please remember that premature birth is not always preventable. Parents should not carry the burden of believing they must have done something wrong.
Were you or someone close to you a parent of a premature baby? What do you wish someone had told you during those first few days?
“My baby’s blood sugar is low. Is it because my breast milk looks like water?”
Imagine being a new parent, watching your baby breastfeed, but seeing only a few drops of watery-looking milk when you squeeze the breast.
Then the hospital tells you your newborn’s blood sugar is low.
Wouldn’t you wonder whether your baby was getting enough nourishment?
That’s exactly what worried a new father who wrote to me from South Africa.
But here’s something every new parent should know: colostrum, the first milk produced after childbirth, is not just water! It is concentrated, nutrient-rich milk, produced in small quantities to meet a newborn’s early feeding needs.
And although low blood sugar can sometimes be associated with inadequate milk intake, it does not automatically mean that a mother’s breast milk has failed.
A newborn with low blood sugar needs prompt assessment and appropriate treatment. Depending on the baby’s condition and glucose level, this may include breastfeeding support, expressed breast milk, donor milk or formula, glucose gel, or intravenous glucose.
So, how can you tell whether your newborn is getting enough milk? And what should happen when the hospital says the baby’s blood sugar is low?
Let’s revisit this father’s question and my original response, with a few important medical updates below.
Q: Hello Dr Ketch, I am writing you all the way from South Africa, a new dad to a 3-day old baby boy. Well I have a concern…baby mama’s breasts seem to be secreting small doses of milk. In fact, yesterday she squeezed them and watery liquid came out, and I got worried that my son drinks water. And this morning baby mama messaged me from hospital (not yet discharged) and told me that baby’s glucose or sugar level is low. My first thought was that he is sucking water and becomes hungry quickly. Is there any way we can improve the situation because we really want him to breastfeed. Thanks.
A: Thanks for writing in and congratulations on your new bundle of joy!
Is your baby sucking water? Well, the first part of breast milk is mainly water with a little fat and is supposed to quench your baby’s thirst (this is why exclusively breastfed babies do not need water to be given to them. Breast milk has sufficient). Thereafter, the richer and creamier hind milk contains the tummy-filling fats and calories. In the first few days of birth, the milk produced, colostrum, is filled with a lot of important nutrients and antibodies that help fight disease. So, if your baby is getting enough breast milk, he is certainly getting more than water. Try and ensure baby spends at least 20 to 45 minutes nursing so as to get the fore and the hind milk. The only problem would be if the feeds are farther than 3 hours apart. In that case, there would be a lot of fore milk and baby may fill up on that before getting to the more filling hind milk. This means he gets hungry more often.
Low sugar level in new born babies does not necessarily suggest there is a problem. When babies are in the womb, they get their glucose (sugar) from their mothers through the umbilical cord and placenta. Some of this glucose is used as an immediate source of energy and the rest is stored in preparation for birth. At birth, with the first couple of hours, baby’s blood sugar level may be low as baby gets used to the idea of being on the ‘outside’. Thereafter, babies can access glucose from their stores until they are feeding well…usually about the 3rd day of life.
Advertisement So, at about the third day, if baby’s mum is not making enough breast milk, then this may become a cause for concern and your wife’s doctors will determine an appropriate course of action which may include giving some formula in the meantime. They would know baby’s mum’s history and know if baby has any other medical condition that could pre-dispose to low blood sugar.
Babies who are more at risk of low blood sugar at birth include: • Babies of diabetic mothers • Babies born with low birth weight (less than 2.5kg) • Babies who were distressed at birth • Family history of children with low blood sugar • Twin or (higher multiple) birth • Babies with mothers taking medications that can put baby at risk of low blood sugar
How can we get mum to make more milk? First, she needs to keep putting baby to the breast…this is the most important and critical step. If the baby starts suckling on the breast, then the milk ejection reflex is stimulated and milk is let down. So, it is important that baby is put to the breast and indeed feed every 3 hours. If she is still in hospital, there will be lactation consultants at hand to help her and ensure that baby is latching on to the breast properly. She should drink sufficient water, rest and get as much help as possible. Some mothers would swear by different foods which increase their milk supply. In Nigeria, a lot of mothers would swear by pap with a lot of milk; others would swear by oatmeal. There’s no proof that these foods increase milk supply, but if you say it works for you, why not?! 😀
“Don’t worry. It’s normal. The yellow eyes will clear.”
That’s what many new mothers hear when they notice their baby’s eyes turning yellow.
And sometimes, the jaundice does clear without treatment. But here’s the problem: you cannot tell how serious newborn jaundice is just by looking at how yellow the baby’s eyes are.
A baby with dangerously high bilirubin may initially look well. Waiting for the baby to become visibly ill could mean waiting too long.
Any newborn who develops jaundice after leaving the hospital should be assessed promptly, ideally the same day. Jaundice appearing in the first 24 hours after birth needs urgent assessment.
In today’s question, a mother notices that her one-week-old baby’s eyes are yellow. She also mentions that her baby initially went three days without passing stool because she wasn’t breastfeeding frequently.
Could the two be connected? And when does newborn jaundice become dangerous?
Let’s revisit this question from a mother and my response. Q: Hello Doctor, thanks for the wonderful work you doing. I’ve been reading your posts since I was pregnant and they really helped me, God bless you. I need your help. I gave birth to a girl a week ago. Her eyes are yellow. At first she spent three days without pooping because I did not breastfeed her a lot but now she poops normal. Is it normal for her to have yellow eyes? Can it be jaundice?
A: Jaundice is a condition in which there is yellowing of the eyes or the skin. So, the condition you describe is jaundice. It can happen in both children and adults. Usually, when old red blood cells are broken down, a yellow pigment, bilirubin is released as part of that process. The bilirubin is removed from the body through urine and stool. It is the bilirubin that gives rise to that yellow colour seen in jaundice.
Other symptoms of jaundice include deep yellow urine and pale stools.
In newborn babies, there are two types of jaundice (neonatal jaundice) that can occur: Physiological jaundice and pathological jaundice.
Physiological jaundice occurs as a natural process of life. While in the uterus, the baby’s bilirubin is removed through the placenta. Once the baby is born, he/she has to handle this bilirubin business by himself/herself J (talk about responsibility immediately after touching down in planet earth!)because his organs are unable to deal with all the bilirubin released from breakdown of red blood cells. As the bilirubin accumulates in blood, jaundice results. Typically, this jaundice appears about 24hours after birth, actually gets worse until the 3rd or 4th day. It would usually have disappeared by the end of one or two weeks.
Pathological jaundice is due to a disease condition like infection, mother and baby’s blood groups not being compatible etc. This is typically present before 24 hours of birth. Indeed, this is the main difference between the two types of jaundice. The one that occurs naturally is seen after 24 hours while the one due to disease is seen before 24 hours…rule of thumb 😀
Jaundice may be mild, disappearing on its own, especially physiologic jaundice. However, sometimes, the yellowness deepens, the baby may develop a high-pitched cry and/or develop arched back. These are dangerous signs and this child should be in a hospital. Indeed, if you observe jaundice in your baby after you have left the hospital, please get it checked out in the hospital just to be sure. Most babies are able to deal with this excess bilirubin on their own without needing treatment. However, some other babies may be put under special lights called phototherapy or in more serious conditions, an exchange blood transfusion may be done (literally, this involves practically exchanging the baby’s bilirubin-filled blood with ‘new’ blood).
The main focus in jaundice is to bring down the level of the bilirubin. If this is not done, it could cross the blood/brain barrier and stain the brain leading to brain damage, a condition called Kernicterus. More frequent feeding is usually suggested as this helps the baby get rid of more bilirubin.
YOU’RE PREGNANT. YOU FEEL FINE. BUT YOUR BLOOD SUGAR COULD BE TOO HIGH WITHOUT YOU KNOWING!
Imagine going for your routine antenatal appointment, feeling perfectly healthy, only to be told that you have diabetes!
No excessive thirst. No frequent urination beyond what you’ve come to expect in pregnancy. Nothing to suggest anything is wrong.
How is that possible?
Well, there’s something called GESTATIONAL DIABETES, and many women who develop it have absolutely no symptoms!
Today is World Diabetes Day, and I want you and every pregnant woman to understand why that blood sugar test at the antenatal clinic is so important.
WHAT IS GESTATIONAL DIABETES?
It is diabetes first diagnosed during pregnancy in a woman who was not previously known to have diabetes.
During pregnancy, hormones produced by the placenta can make it harder for insulin to work properly. If your body cannot produce enough insulin to compensate, your blood sugar rises.
And you may feel completely fine!
WHY SHOULD YOU BE CONCERNED?
When your blood sugar remains too high during pregnancy, your baby may grow larger than expected.
This can increase the risk of a difficult delivery, including shoulder dystocia, where the baby’s shoulder becomes stuck during birth.
Your baby may also develop LOW blood sugar after delivery, particularly because their body has been producing extra insulin.
For the mother, gestational diabetes increases the risk of high blood pressure complications, including pre-eclampsia, and Caesarean delivery.
It also increases the likelihood of developing type 2 diabetes later in life.
WHEN SHOULD YOU BE TESTED?
Most pregnant women are screened for gestational diabetes between 24 and 28 weeks of pregnancy.
If you have certain risk factors, your healthcare provider may recommend testing earlier.
And please, don’t skip the test simply because you feel healthy!
WHAT HAPPENS IF YOU HAVE GESTATIONAL DIABETES?
First, don’t panic. Many women with gestational diabetes go on to have healthy pregnancies and healthy babies.
Treatment usually involves making appropriate changes to what you eat, monitoring your blood sugar and staying physically active when it is safe to do so.
Some women will also need medication, including insulin, to keep their blood sugar within the recommended range.
Please don’t starve yourself to make your baby smaller! The goal is to manage your blood sugar while ensuring that you and your baby receive adequate nutrition.
DOES THE DIABETES DISAPPEAR AFTER DELIVERY?
Gestational diabetes often resolves after childbirth, but that doesn’t mean you should forget about it.
You should have a blood sugar test, usually a 75-g oral glucose tolerance test, 4–12 weeks after delivery.
Even if the result is normal, you will need periodic diabetes screening because your risk of developing type 2 diabetes remains higher.
So, the next time your antenatal clinic asks you to check your blood sugar, please take that test seriously.
Feeling healthy is wonderful. But it cannot tell you what your blood sugar is doing.
Have you ever been diagnosed with gestational diabetes, or do you know someone who was? Did they have any symptoms before the diagnosis?
YOUR BABY IS JUST 2 WEEKS OLD AND HAS A FEVER. PLEASE DON’T GIVE PARACETAMOL AND WAIT!
A mother once sent me this question:
“Good evening Doctor. My baby is just 2 weeks of age and always has this high fever.”
Now, I know how tempting it can be to give a baby some paracetamol, remove a few layers of clothing and wait to see whether the temperature comes down.
But remember that fever in a newborn can be the first sign of a serious infection, even when the baby looks perfectly fine.
Babies this young can deteriorate very quickly. Sometimes, there may be no obvious symptoms apart from the fever.
SO, WHAT COUNTS AS A FEVER?
For a baby younger than 3 months, a temperature of 38°C (100.4°F) or higher requires immediate medical assessment.
Use a digital thermometer. All of us became used to this during COVID, right? ☺️ A rectal temperature is the most accurate measurement in young infants when taken correctly. If your baby feels unusually hot or you suspect a fever, seek medical advice immediately rather than delaying care while trying to get a perfect reading.
BUT WHAT IF THE BABY WAS WRAPPED IN TOO MANY CLOTHES?
Yes, excessive clothing can make a baby overheated.
Remove unnecessary layers and move the baby to a comfortably cool environment.
However, if a newborn has a measured fever, please do not assume it is simply because of the weather or too many clothes.
A fever may be caused by an infection that requires urgent investigation and treatment.
SHOULD YOU GIVE PARACETAMOL FIRST?
Not without medical advice.
Paracetamol may lower the temperature temporarily, but it does not treat a serious bacterial infection. It may also make parents think the problem has resolved when the baby still needs urgent care.
Do not delay going to hospital because you are waiting to see whether medication works.
WHAT ABOUT TEPID SPONGING?
Routine tepid sponging is no longer recommended for treating fever in children. It can make babies uncomfortable and does not prevent febrile seizures (fever convulsions).
And febrile seizures are uncommon in newborns; they typically occur in older infants and young children.
WATCH FOR THESE ADDITIONAL DANGER SIGNS:
– Poor feeding or refusing breast milk. – Unusual sleepiness or difficulty waking. – Fast or difficult breathing. – Weak or unusual crying. – Seizures. – An unusually low temperature, particularly if the baby seems unwell.
These signs also require urgent medical attention, even if there is no fever.
Did you know that a fever in a newborn is treated differently from a fever in an older child?
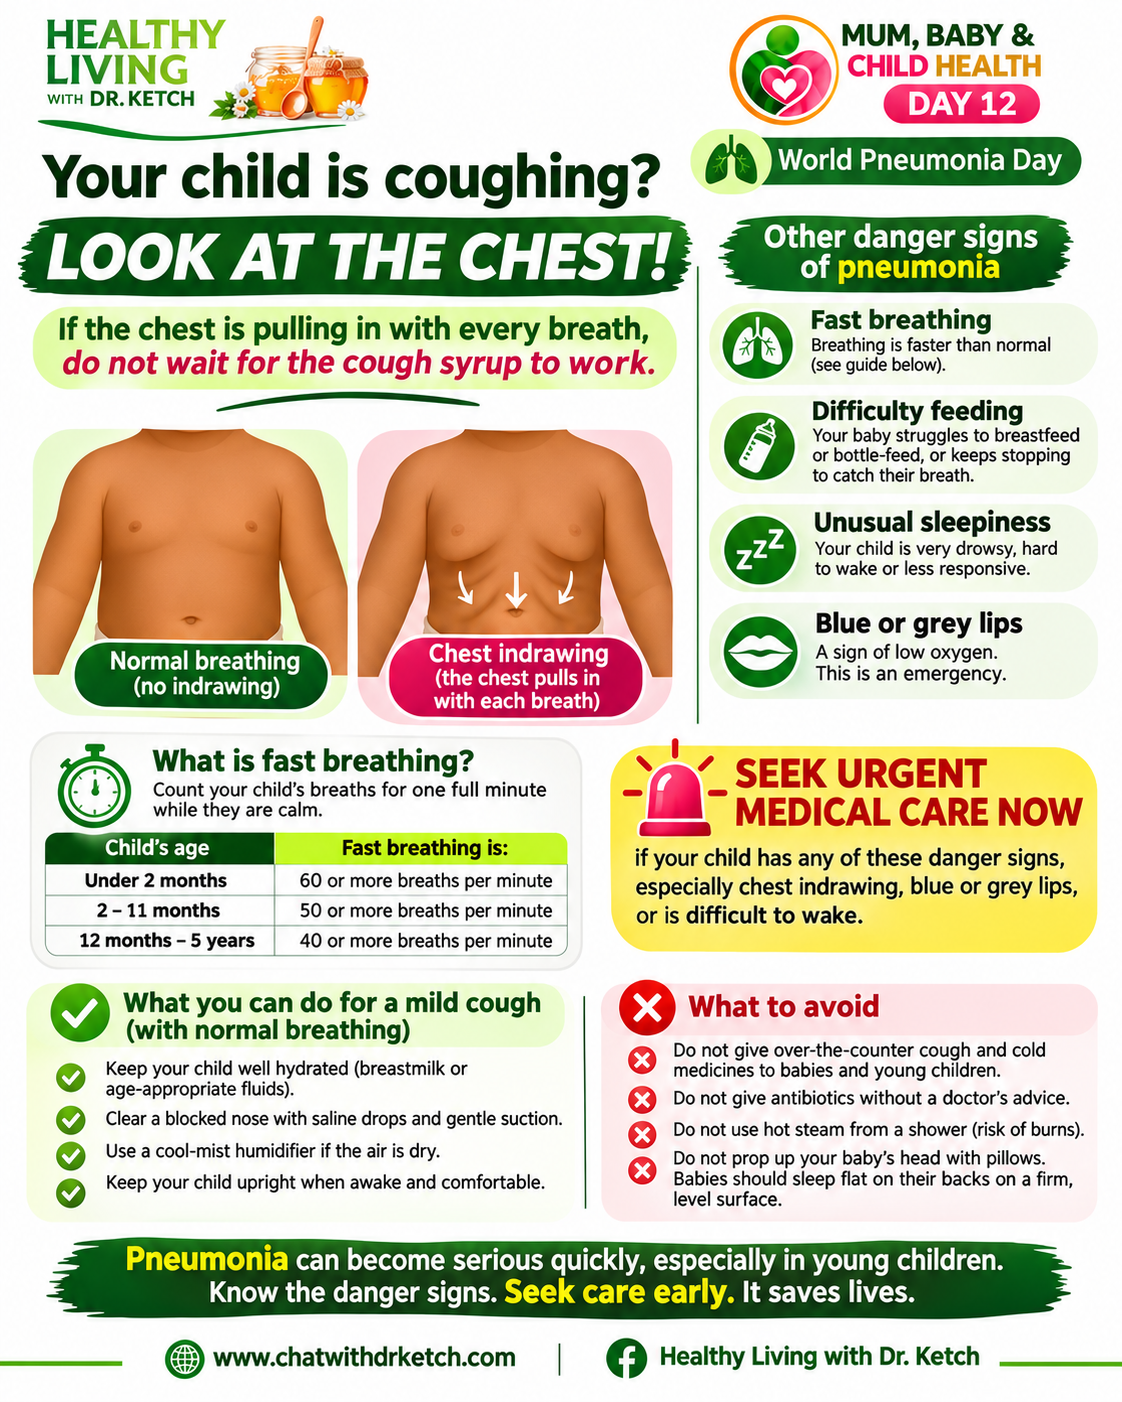
YOUR CHILD IS COUGHING. ARE THE RIBS DISAPPEARING WITH EVERY BREATH?
Please, look at your child’s chest the next time they have a cough. What you see could save their life.
Today is World Pneumonia Day, and there’s something I want every parent to know.
A child with pneumonia may have a cough and fever. But sometimes, the most worrying sign is how the child is breathing.
LOOK OUT FOR THESE WARNING SIGNS:
1. The chest is pulling inward.
Watch the lower part of your child’s chest when they breathe in. Is the area below the ribs sinking inward instead of moving outward?
This is called chest indrawing. It may mean your child is struggling to breathe. Seek urgent medical care.
2. Your child is breathing unusually fast.
Count the breaths for one full minute while your child is calm.
For a child with a cough, fast breathing means:
Under 2 months: 60 or more breaths per minute.
2–11 months: 50 or more breaths per minute.
12 months–5 years: 40 or more breaths per minute.
Fast breathing needs prompt medical assessment. Don’t wait for your child to develop a high fever.
3. Your baby is struggling to feed.
If your baby cannot breastfeed or drink normally because they are struggling to breathe, seek emergency care.
4. Your child is unusually sleepy or difficult to wake.
A child who is barely responding, unusually floppy or too weak to feed needs emergency medical attention.
5. The lips or tongue look blue or grey.
This may mean your child is not getting enough oxygen. This is an emergency.
WHAT ABOUT COUGH SYRUP?
Cough syrup will not treat pneumonia. Over-the-counter cough and cold medicines can also be dangerous for young children.
Not every cough requires antibiotics, but bacterial pneumonia may need prompt antibiotic treatment.
If your baby is younger than three months and has a temperature of 38°C or higher, seek immediate medical assessment.
Remember: A child does not need to have every warning sign before you seek help. Severe difficulty breathing, blue or grey lips, or difficulty waking your child are reasons to seek emergency care immediately.
Have you ever noticed a child’s chest pulling inward while they were breathing? Did you know what it meant?
YOUR DOCTOR SAYS YOUR UNBORN BABY IS TOO BIG. SHOULD YOU START EATING LESS?
A pregnant mother once asked me this question:
“Doc, I’m in my last trimester and my doctor says my baby is big. I’ve decided to start taking tea every day. Is it safe?”
My concern wasn’t really the tea. It was the possibility that she was trying to stop her baby from growing by changing what she ate or drank.
First, let’s understand what your doctor means when they say your baby is big.
An ultrasound scan can estimate your baby’s weight, but it cannot weigh the baby. These estimates aren’t always accurate, especially towards the end of pregnancy.
Some babies are naturally bigger than others. But there are factors that increase the likelihood of having a large baby, including gestational diabetes, diabetes that existed before pregnancy, excessive pregnancy weight gain, maternal obesity and having previously delivered a large baby.
So, should you start eating less?
No! Skipping meals, starving yourself or drinking slimming teas will not safely make your baby smaller. Your baby still needs nutrients to grow and develop.
What you need is a discussion with your doctor about why your baby may be large.
If you have gestational diabetes, controlling your blood sugar through appropriate nutrition, physical activity and medication when necessary can help reduce complications.
Does a big baby automatically mean a Caesarean section?
Not necessarily! Many women with suspected large babies can still deliver vaginally. Your obstetrician will consider the estimated weight, whether you have diabetes, your previous deliveries and other relevant factors before recommending the safest delivery plan.
A very large baby can increase the risk of a difficult delivery, including shoulder dystocia, where the baby’s shoulder becomes stuck after the head is delivered. Some babies, especially those born to mothers with diabetes, may also develop low blood sugar after birth.
Here’s what I want you to remember: If your doctor says your baby is too big, don’t respond by eating less. Ask about your blood sugar results, how the baby’s weight was estimated and what this means for your delivery.
Have you ever been told during pregnancy that your baby was too big? Was the baby actually that big at birth?
The moment she lies down, the burning climbs from her stomach into her chest.
Now she is sitting upright at 2 a.m., pregnant and desperate to sleep.
Pregnancy hormones relax the muscle that normally keeps stomach acid down. As the baby grows, pressure on the stomach makes it easier for acid to travel upwards.
Relief at night often starts with dinner.
Eat smaller portions and finish your last meal about three hours before bed. Sit upright while eating and remain upright afterwards.
Raise your head and shoulders when you sleep. Lying on your left side may also reduce the reflux.
Your trigger may be different from someone else’s. Keep a short food diary and look for a pattern. Fatty meals, spicy foods and caffeine are common culprits. Chocolate, tomatoes and citrus can also trigger symptoms.
If these changes are not enough, speak to a doctor or pharmacist about an antacid or alginate that is suitable during pregnancy. Some products are unsuitable, so mention that you are pregnant.
Keep antacids at least two hours away from iron or folic acid supplements because they can reduce absorption.
Please contact your maternity team if the heartburn continues despite these changes or you have difficulty swallowing.
After 20 weeks, severe pain under the ribs or “heartburn” that refuses to settle needs urgent assessment. A severe headache or changes in vision make that call even more important.
When a pregnant woman’s water breaks, it does not always pour out in the dramatic gush we see in films. Sometimes it is a persistent trickle that repeatedly wets her underwear.
Urine often has its familiar smell and may escape when you cough or sneeze. Normal pregnancy discharge is commonly clear or milky and may feel creamy.
Amniotic fluid is often clear or pale. It may continue leaking even after you have emptied your bladder. These clues can help, but they cannot confirm what the fluid is.
If you think your water may be leaking, put on a clean maternity pad and contact your maternity unit or the nearest hospital with maternity services. Do not insert a tampon.
Before 37 weeks, a leak may mean that the sac surrounding the baby has opened too early. This can expose the baby to infection and may lead to premature birth.
Go urgently if the fluid is green, brown, bloody or has a bad smell. Seek help if you develop fever or abdominal pain, or your baby’s movements reduce.
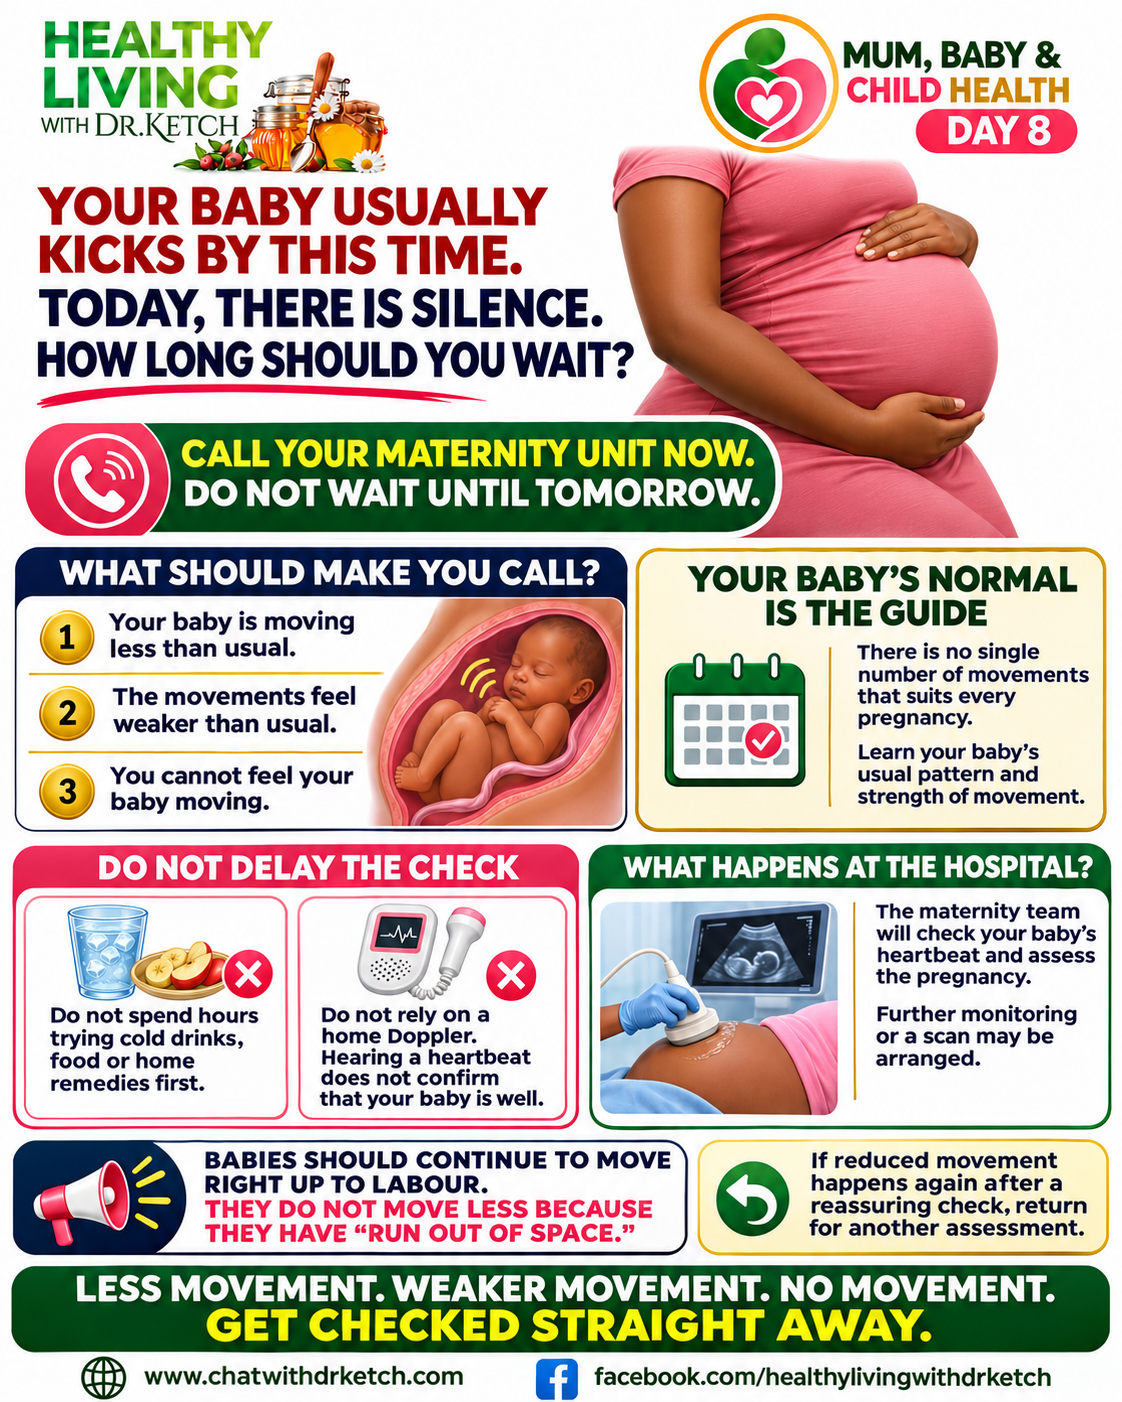
She knows her baby’s routine. By this time, the kicks usually begin.
Today, her hand rests on her belly and…..nothing.
Call your maternity unit or the hospital where you receive antenatal care now. If you cannot reach them, go to the nearest hospital with maternity services. Do not wait until morning.
There is no movement number that fits every pregnancy. What’s important is your baby’s usual pattern and the strength of those movements.
Call for assessment when your baby moves less than usual. Call when the movements feel weaker. Call when you can no longer feel movement. Call, if you’re not sure.
Do not delay assessment while trying food or cold drinks at home. A home Doppler cannot tell you whether your baby is well. Hearing a heartbeat does not replace a proper check.
At the hospital, the maternity team will check your baby’s heartbeat and assess the pregnancy. They may arrange further monitoring or a scan.
Your baby should continue moving right up to labour. The movements may feel different as pregnancy advances, but they should still be present.
If reduced movement happens again after a reassuring assessment, please return for another check